ENT specialists diagnose breathing problems during sleep through a focused medical history, a physical exam of the head and neck airways, and sleep testing that records airflow overnight. At Texas Sinus and Snoring in Spring, Dr. Ben Cilento uses this pathway so snoring, nasal blockage, and sleep apnea are not treated as the same problem. The evaluation pinpoints where air is restricted, how often breathing slows or stops, and the exact cause and severity – paving the way for effective treatment.
Understanding Sleep-Related Breathing Problems
Waking up tired, struggling with daytime fatigue, or being told you snore loudly can signal an underlying sleep-related breathing disorder. These issues impact overall health and quality of life.
What Are Sleep-Related Breathing Disorders?
Sleep-related breathing disorders involve abnormal airflow through the nose or throat during sleep. Soft tissue vibrates, the airway narrows, and breathing can pause – preventing restorative, deep sleep.
Common forms include:
Obstructive sleep apnea (OSA), where the airway repeatedly collapses or becomes blocked
Heavy snoring – involves loud, disruptive vibration of throat tissue without pauses in breathing
Upper airway resistance syndrome (UARS) – causes repeated breathing effort and brief arousals that fragment sleep without meeting the criteria for apnea
Central sleep apnea – when the brain fails to send proper signals to breathe rather than because of a physical airway blockage
Nasal blockage often starts the pattern. When the nose is congested, the mouth opens and the tongue and soft palate fall backward more easily, which is why an ENT looks at the entire airway rather than the throat alone. Nasal breathing and sleep quality are tightly linked. Signs are often noticed by a bed partner or show up during the day. Some patients feel they slept a full night and still wake unrefreshed.
The Role of ENT Specialists in Diagnosing Sleep Breathing Issues
An Ear, Nose, and Throat (ENT) specialist is uniquely qualified to diagnose and treat sleep-related breathing disorders. As an expert in the entire airway – from the tip of the nose to the throat and on toward the lungs – an ENT can identify the physical obstructions that cause these problems.
When to See an ENT Specialist
Schedule an evaluation if you or a partner notice common symptoms, if you feel tired despite a full night’s sleep, or if snoring is disrupting your household. Patients in Spring, TX, often come to us after years of attributing fatigue to stress or age. An airway exam can show a mechanical cause that sleep hygiene alone will not fix.
See an ENT if you have:
Loud snoring, broken sleep, or low daytime energy
Witnessed pauses in breathing or waking with a gasp
Chronic stuffiness, mouth breathing, or a history of sinus trouble
Excessive daytime sleepiness that interferes with work or daily activities
Morning headaches
An ENT Surgeon is trained to inspect the structures that move air from the nostrils to the lungs. An ENT can determine whether the issue is simple snoring or a more significant condition, such as sleep apnea.
ENT Evaluation Process
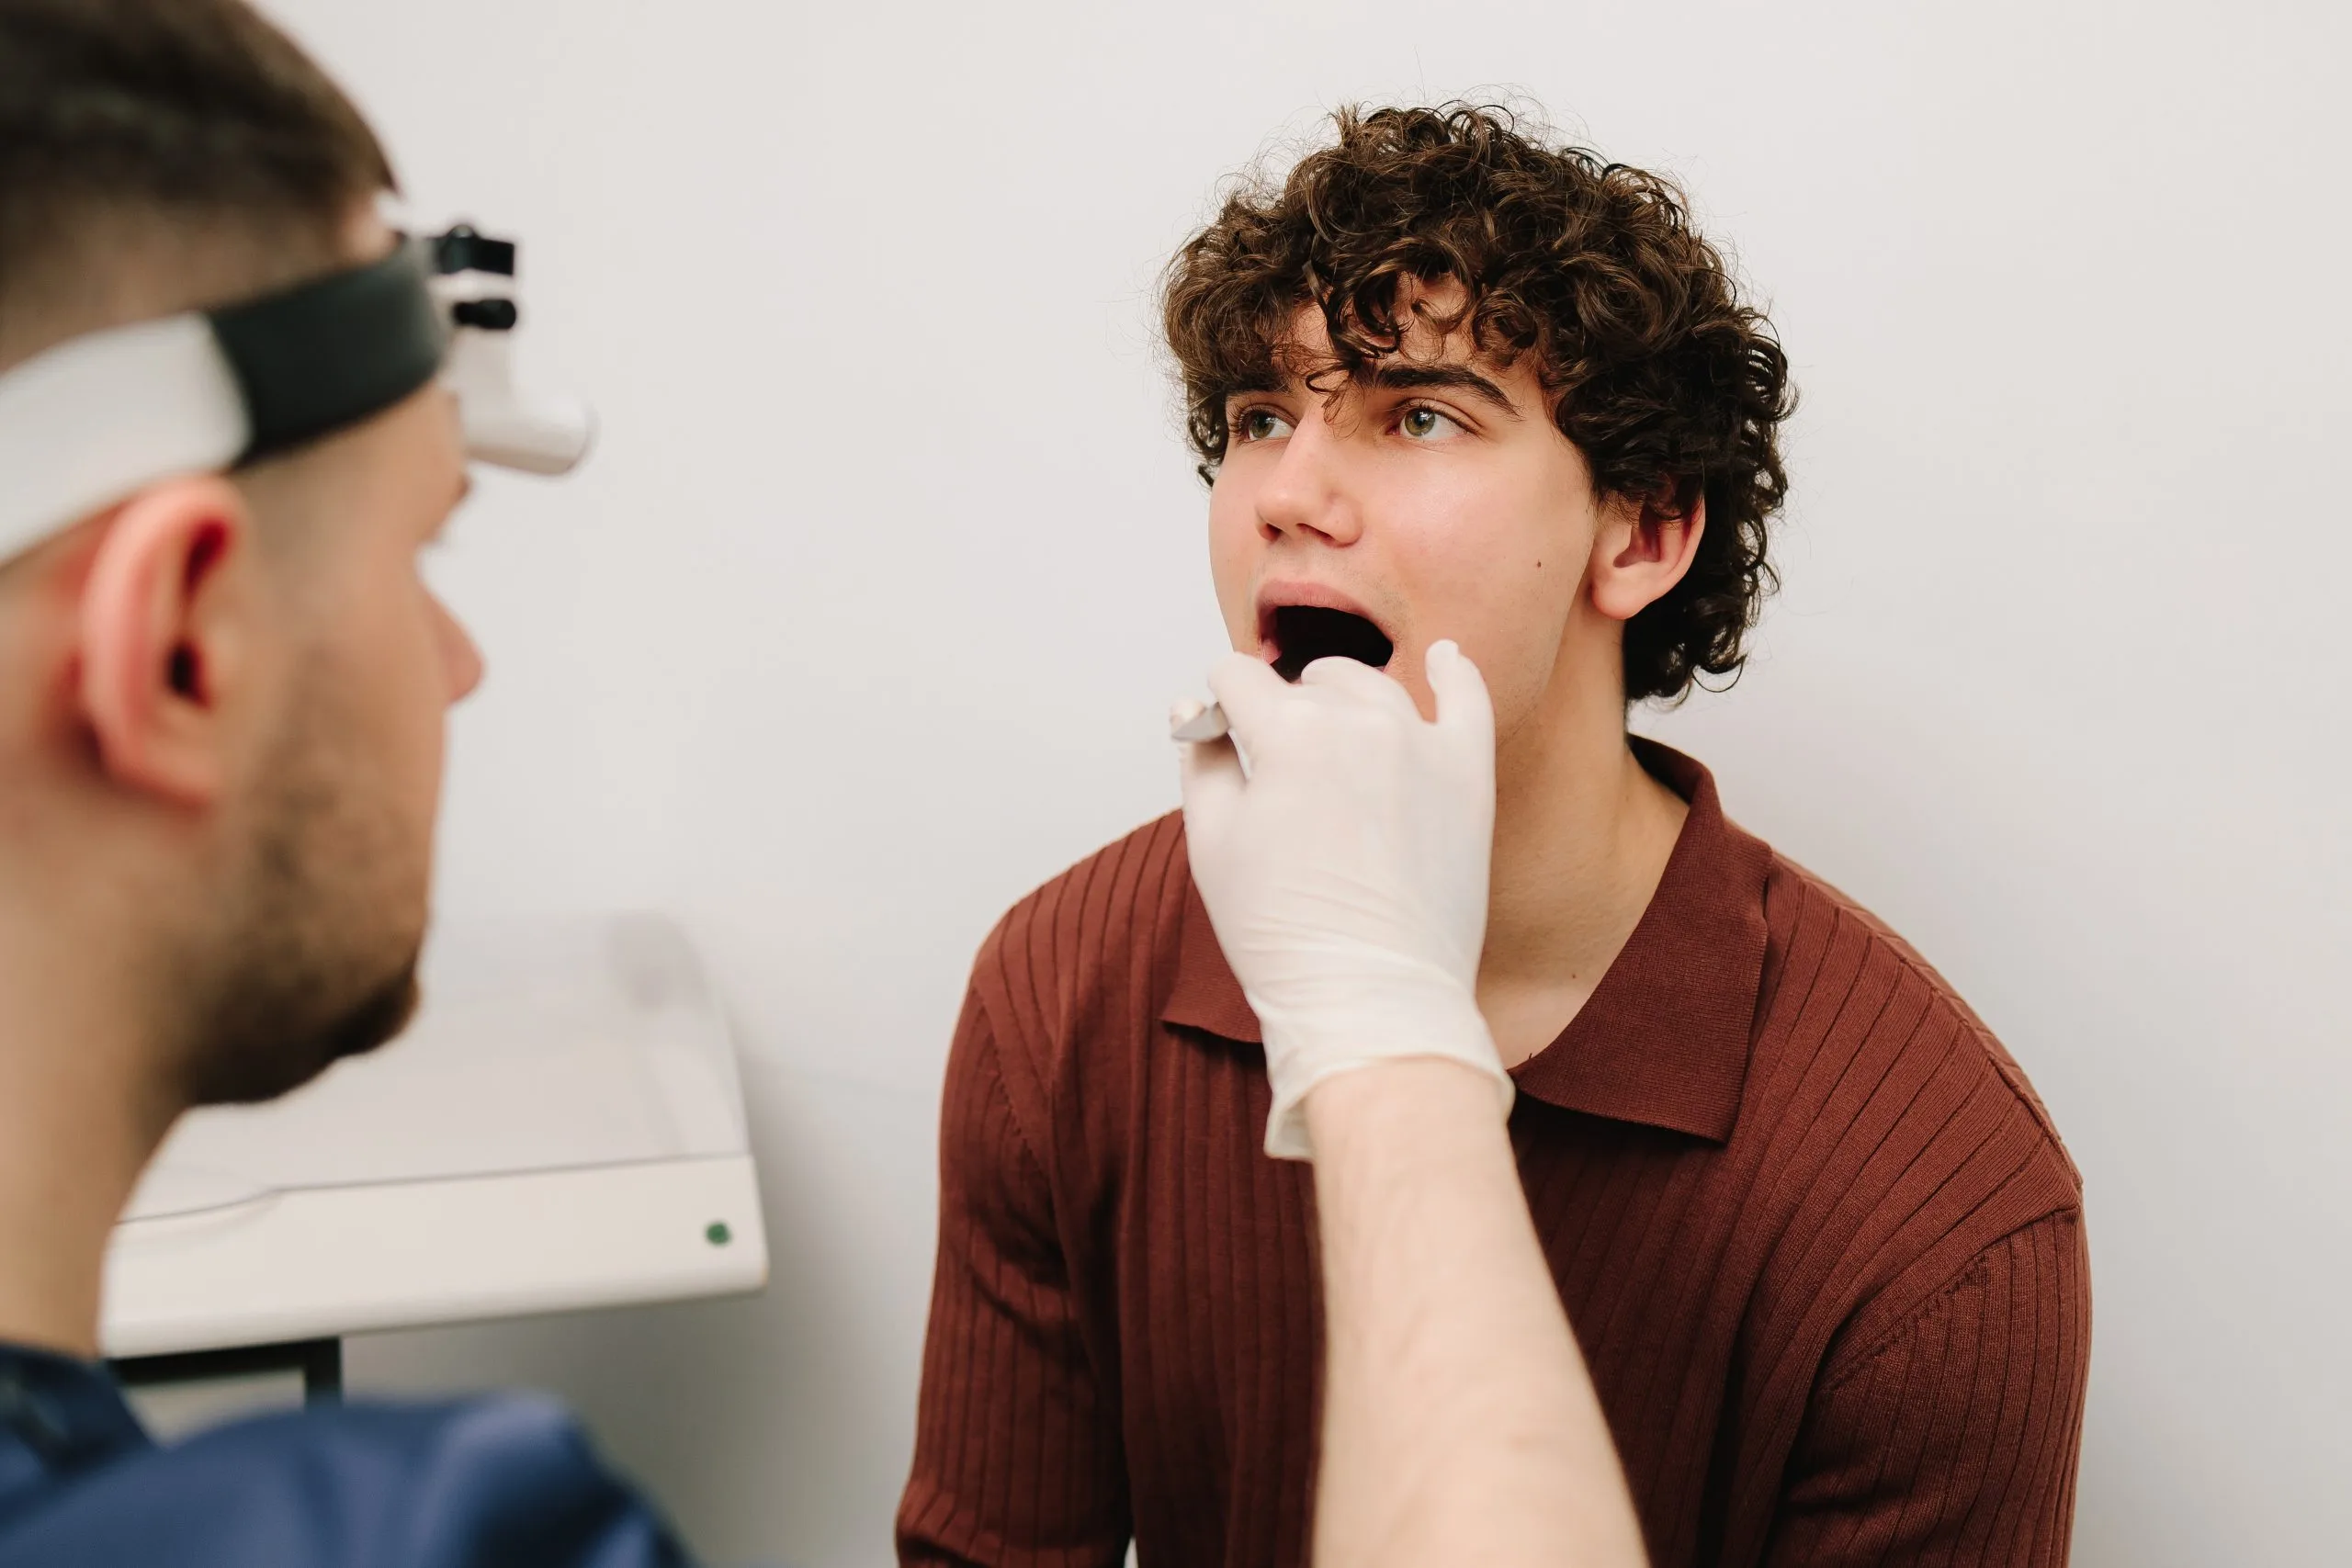
The visit at our Spring office starts with listening. Dr. Ben Cilento discusses your symptoms, sleep habits, and overall health history, and then examines your entire airway in a single evaluation. That prevents a nasal problem from being missed while attention stays solely on the throat, or vice versa.
The exam covers:
Septum, turbinates, and nasal valves
Tonsils, tongue base, and palate
Nasal passages, mouth, and throat for structural blockage
Findings guide whether a sleep study is the next step and which treatment path may be most helpful later.
Snoring vs. Sleep Apnea: Key Differences
While nearly all patients with sleep apnea snore, not all snoring is caused by sleep apnea. Snoring is the sound produced by vibrating tissue when airflow is partially obstructed. Sleep apnea involves complete or significant blockages that stop breathing for ten seconds or longer, multiple times per hour – your brain briefly wakes you to resume breathing, fragmenting sleep and dropping oxygen without you realizing it.
Snoring can be caused by:
When Snoring Signals a Bigger Problem
Simple snoring is often consistent and rhythmic. Apnea-related snoring is typically much louder and interrupted by periods of silence followed by loud gasps, snorts, or choking sounds.
Snoring that is loud, nightly, and accompanied by gasping, morning headaches, or unrefreshing sleep warrants testing. A blocked nose can make snoring worse, even when the throat is the main site of collapse – nasal valve weakness and turbinate swelling are common findings we see during exams.
Signs You Should Seek Professional Help
If your snoring is accompanied by any of the following, it is crucial to get evaluated:
Excessive daytime sleepiness that interferes with work or daily activities
Morning headaches
High blood pressure, especially if it is hard to control
A partner witnessing you stop breathing during sleep
Waking choking
Inability to stay alert while driving or working
Persistent nasal congestion
Years of untreated snoring
These symptoms suggest that snoring is part of a larger medical issue. Do not wait for symptoms to become extreme. Earlier testing makes it easier to match the right therapy to the right site of obstruction.
How ENT Specialists Diagnose Breathing Problems During Sleep
The diagnostic process is methodical. It aims to understand not just if you have a breathing problem, but why and where it is located within your airway.
Medical History and Physical Examination
Diagnosis begins with history. Dr. Ben Cilento documents symptoms, lifestyle, sleep patterns, daytime energy, and existing medical conditions. This step tells us whether the problem is likely nasal, throat-based, or both – and whether an at-home sleep study is appropriate.
History covers:
Snoring volume and sleep position
Witnessed pauses, reflux, and allergy symptoms
Prior sinus surgery and medicines that affect sleep
Nasal blockage, allergies, and sinus infections
Daytime sleepiness and morning symptoms
The physical exam maps the airway for features that contribute to obstruction:
A deviated or crooked septum
Enlarged or swollen nasal turbinates
Valve collapse on gentle inspiration
Large tonsils or adenoids
An elongated or thick soft palate or uvula
A large tongue base or a narrow lower jaw
Nasal and Airway Assessment
To get a clear view of the airway, we may use nasal endoscopy. This painless procedure passes a small, flexible camera through the nose to examine the nasal passages, the back of the throat, and the vocal cords. It shows structural blockages in the nose and throat – critical for planning targeted treatments like nasal valve reconstruction or septoplasty.
We assess:
The septum
The turbinates, including turbinate hypertrophy that can block a large share of the nasal passage
The internal and external nasal valves, including collapse visible when a patient inhales
The throat exam looks at the palate, uvula, tonsils, and tongue base. Together, the nasal and throat findings explain why some patients snore and others stop breathing. These findings also guide later treatment planning, including turbinate reduction.
Use of Sleep Studies
If the initial evaluation suggests a high probability of sleep apnea, the next step is typically a sleep study, or polysomnography. A sleep study measures what the exam cannot see at night and provides objective proof of a sleep-related breathing disorder.
It records:
Airflow, breathing patterns, and respiratory effort
Blood oxygen levels
Heart rate, and in some tests, heart rhythm and sleep position
Brain activity and body movements
The study determines whether events are hypopneas, apneas, or simple snoring and grades their severity. We use those numbers with the airway exam so treatment targets the true blockage rather than a guess.
Types of Sleep Studies
There are two main types of sleep studies, and the right one depends on your specific situation and medical history.
In-Lab Sleep Studies (Polysomnography)
The traditional method is an in-lab sleep study at a specialized sleep center, where technicians monitor you overnight with a variety of sensors. It is the most comprehensive type of sleep study and the most complete recording of sleep stages and breathing events, though it can be inconvenient for many patients.
It is useful when:
Sensors track:
At-Home Sleep Studies
At Texas Sinus and Snoring, we offer the convenience of an At-Home Sleep Study. You sleep in your own bed for one night using a portable monitoring device that is simple to use and less bulky than a lab hookup.
The device collects data on:
Breathing and airflow
Oxygen levels
Respiratory effort
Results are downloaded and analyzed by our team, then reviewed with exam findings. This option is often the first test when obstructive sleep apnea is the main concern and is highly effective for diagnosing most cases of OSA. Patients in Spring, TX, can be evaluated without spending the night in a lab.
How Sleep Apnea Is Diagnosed
Once the sleep study is complete, the data is analyzed to determine if you have sleep apnea and how severe it is. Sleep apnea is diagnosed when a sleep study shows repeated drops in airflow that meet clinical criteria.
Criteria and Diagnostic Tools
The primary metric is the Apnea-Hypopnea Index (AHI), which counts the average number of apnea (complete cessation of breathing) and hypopnea (partial blockage or very shallow breathing) events per hour of sleep. Blood oxygen saturation drops and symptom reports complete the picture. Mild, moderate, and severe categories are based on those counts and how you feel during the day.
Normal: Fewer than 5 events per hour
Mild Sleep Apnea: 5 to 15 events per hour
Moderate Sleep Apnea: 15 to 30 events per hour
Severe Sleep Apnea: More than 30 events per hour
Tools include:
None of these stands alone. Numbers without anatomy miss the blockage. Anatomy without numbers misses severity.
The Role of ENT in Sleep Apnea Diagnosis
An ENT’s role goes beyond reading the sleep study report. Dr. Ben Cilento combines the AHI score and oxygen data with findings from your physical exam and airway assessment. This maps where the airway narrows, how that matches severity, and the specific anatomical reasons behind it.
That step decides whether the next move is:
Diagnosis is not only a label. It is a map of the obstruction, which is essential for recommending the most effective treatment plan for your unique anatomy.
Next Steps After Diagnosis
Receiving a diagnosis is the first step toward better sleep and improved health. Once we confirm a diagnosis and understand the cause, we walk you through treatment options matched to the site and severity of blockage.
Treatment Options and Referrals
At Texas Sinus and Snoring, we offer a wide range of advanced treatments tailored to the individual. The plan is built from your anatomy, not a single default device. Some patients need more than one site addressed.
Nasal options can include:
Sleep apnea care may include:
Oral appliances: Custom-fit devices that reposition the jaw to keep the airway open
CPAP Therapy: A machine that delivers continuous air pressure through a mask to keep the airway open throughout the night
AIRLIFT Procedure: A minimally invasive treatment to support and open the airway
Surgical procedures: Septoplasty or turbinate reduction to correct structural issues in the nose
Ongoing Care and Monitoring
Treating a sleep-related breathing disorder is a partnership. Diagnosis is not the last visit. We work with you to find the right solution and provide ongoing care so treatment remains effective.
Follow-up includes:
Reassessing snoring, energy, and nasal airflow after treatment
Repeat testing to confirm that breathing events have dropped
Appointments and adjustments based on symptoms and data
Chronic rhinitis, sinus disease, and allergies can change the airway over time, so follow-up keeps the plan current. Our team monitors progress to help you achieve lasting relief.
Conclusion
Diagnosing a sleep-related breathing problem is a precise, multi-step process: history, airway exam, and sleep testing. That sequence separates snoring from apnea, indicates whether the nose, the throat, or both are involved, and allows an ENT specialist to identify the root cause. With a clear diagnosis, a personalized treatment plan can target the underlying cause so you can breathe easier, sleep better, and improve your overall health in a measurable way.